If concentration problems improve the moment you feel calm or you’re doing something you enjoy, that points toward anxiety driving your attention away from the task at hand. If the same restlessness, disorganization, and difficulty finishing things have shown up since childhood, across school, work, and home, that pattern points toward ADHD. Many adults have both, with research estimating that 25% to 50% of people with ADHD also meet criteria for an anxiety disorder, so a proper screening or professional evaluation is the next useful step.
TL;DR:
- Clinicians look for ADHD symptoms before age 12 and impairment in at least two settings, using records or trusted people to corroborate childhood history.
- Some ASRS hyperactivity items do not clearly distinguish anxiety from ADHD, so screening scores cannot confirm either diagnosis on their own.
- In one anxiety clinic sample, 27.9% of 129 patients met criteria for adult ADHD, supporting screening for the second condition after either diagnosis.
- Current guidance favors treating the condition causing the greatest distress or disruption first, then adding medication or therapy as needed while monitoring both symptom patterns.
- Before an assessment, collect school records, ask someone who knew you as a child for observations, and note recent impairment at work and home.
The reason ADHD and anxiety get confused so often is that they can look identical from the outside. Someone staring blankly at a laptop screen, missing a deadline, or forgetting a conversation detail could be dealing with either condition, or both at once. The overlap happens because worry and attentional dysregulation both interrupt your ability to focus, just through different mechanisms. With anxiety, your mind is occupied by a worry loop that competes for the same mental bandwidth you’d otherwise use for the task. With ADHD, the attention system itself struggles to regulate what gets prioritized, regardless of how you feel emotionally.
That distinction matters because the overlapping symptoms include:
ADHD tends to carry its own fingerprint beyond these shared symptoms. We see a lifelong pattern rather than something that appeared in adulthood, along with executive dysfunction: forgetfulness about appointments or belongings, chronic lateness, and trouble estimating how long tasks will take. Impulsivity often shows up too, whether that’s interrupting conversations, making quick purchases, or switching tasks mid-stream. Paradoxically, many adults with ADHD also describe hyperfocus, where an interesting project can absorb hours without any sense of time passing, even while unrelated obligations slip entirely.
Anxiety has its own signature. Worry tends to be persistent and often disproportionate to the actual situation, escalating sharply around specific triggers like a performance review, a social event, or a health scare. Physiological arousal often comes along with it: a racing heart, sweating, muscle tension, or stomach upset. Some people experience full panic attacks, with sudden, intense fear accompanied by physical symptoms that can feel alarming in the moment.
Everyday examples make the difference easier to spot. A person with ADHD might make careless mistakes at work regardless of how relaxed or motivated they feel, simply because sustained attention to repetitive detail is hard for them. A person with anxiety might perform fine on familiar tasks but fall apart during a high-stakes exam because worry about failing consumes the mental resources needed to recall what they studied. At bedtime, someone with anxiety often lies awake rehearsing conversations or worst-case scenarios, while someone with ADHD might avoid winding down at all, bouncing between unfinished tasks until exhaustion forces sleep. Both patterns can leave a task unfinished, but the reason behind it is different, and that reason is what a clinician is listening for.
Clinicians rely on a handful of specific clues rather than a single symptom checklist, because so many surface-level complaints overlap. Four factors carry particular weight: when symptoms started, where they show up, whether they shift with your emotional state, and what collateral information reveals.
Before an assessment, it helps to sit with a few direct questions: Does my mind wander even when I’m relaxed and interested in what I’m doing? Did I struggle with this before I had responsibilities that could make anyone anxious? Do people who’ve known me a long time say this has always been part of who I am, or do they connect it to a specific period of stress? Honest answers to these questions give a clinician far more to work with than a simple symptom list.
Co-occurrence between these two conditions is common, not the exception. Research indicates that 25% to 50% of people with ADHD also meet criteria for an anxiety disorder, and the same body of research found that in one anxiety clinic sample of 129 patients, 27.9% also met criteria for adult ADHD. That overlap runs in both directions.
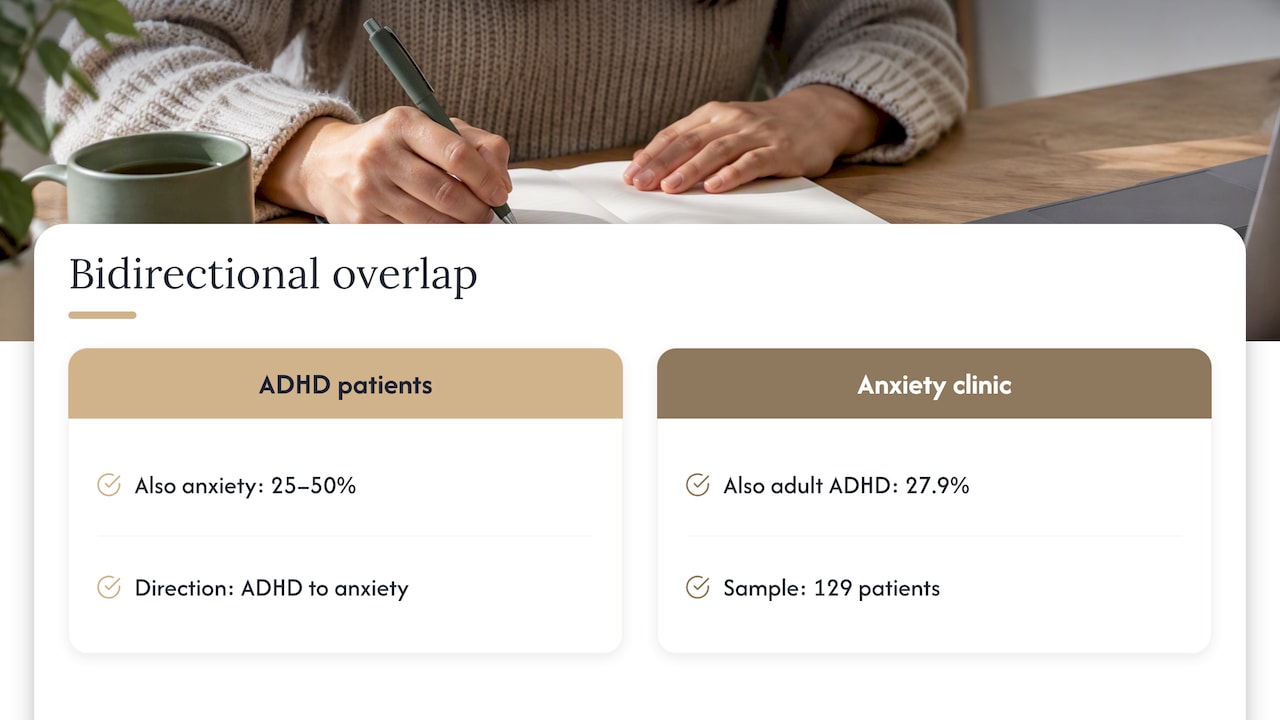
Nearly one in three patients at an anxiety clinic also met criteria for adult ADHD, according to a clinical sample analysis, underscoring why a diagnosis of one condition should prompt screening for the other rather than closing the door on further inquiry.
The relationship works both ways. Living with undiagnosed or poorly managed ADHD often generates its own anxiety: the chronic stress of missed deadlines, forgotten commitments, and underperforming relative to your own expectations builds into a persistent worry about falling short again. Meanwhile, anxiety can worsen attention and working memory on its own, making an underlying attention difficulty look more severe than it would be in isolation. Each condition can amplify the other, which is part of why self-diagnosis from a symptom list rarely gives a clear answer.
This overlap has real clinical consequences. A retrospective claims analysis found that patients with ADHD plus comorbid anxiety and/or depression experienced more frequent changes to their ADHD medication regimen and higher excess healthcare costs over a 12-month period compared with patients who had ADHD alone. That pattern suggests that when both conditions are missed or treated in isolation, people cycle through more trial and error before finding a plan that actually works, which is exactly why a careful, comprehensive assessment upfront matters so much.
Clinicians lean on validated screening instruments to structure what might otherwise be a vague conversation about symptoms. The most widely used adult ADHD screen is the Adult ADHD Self-Report Scale, or ASRS, a short questionnaire covering inattention and hyperactivity-impulsivity symptoms. It’s useful for flagging who might warrant a fuller evaluation, but it has a notable limitation: research examining the ASRS in adults with clinically diagnosed anxiety found that some items, particularly within the hyperactivity factor, don’t clearly separate ADHD symptoms from anxiety symptoms. A restless, keyed-up feeling can score the same on an ASRS item whether its root cause is an attention disorder or a persistent worry state, which is exactly why clinicians dig deeper into whether those symptoms exist independently of anxious arousal.
On the anxiety side, common screens include the GAD-7, a brief measure of generalized anxiety symptoms, along with broader distress measures like the DASS-21 and the K10, which capture overlapping dimensions of anxiety, depression, and general psychological distress. None of these tools diagnoses anything on its own. They’re a starting point for conversation, not a verdict.
What actually confirms a diagnosis is the harder evidence: proof of childhood onset and impairment across multiple settings, gathered through clinical interview, history, and sometimes collateral report. The National Institute of Mental Health notes that a thorough evaluation needs to rule out other explanations, including anxiety, sleep disorders, and medical conditions, before ADHD is confirmed.
If you’re preparing for an assessment, a little groundwork goes a long way:
Pro Tip: Keep a log of when your focus is sharpest and when it falls apart; noticing the pattern yourself can help answer the clinician’s questions.
Treatment approaches differ meaningfully depending on which condition is driving the picture, which is exactly why getting the diagnosis right matters. ADHD is most often treated with stimulant medication alongside strategies for executive function support, such as externalizing tasks through planners or reminders. Anxiety typically responds to SSRIs, cognitive behavioral therapy, or a combination of both, with CBT for anxiety focused on identifying and restructuring worry patterns. When both conditions are present, clinicians often adapt CBT techniques to address executive dysfunction alongside anxious thinking, rather than treating them as entirely separate problems.
Here’s where it gets genuinely complicated. Clinicians describe a real treatment conundrum when both conditions coexist: stimulant medication often improves the executive function problems at the core of ADHD, but in some people it can heighten anxious arousal. SSRIs calm anxiety but do nothing for the attentional and organizational struggles of ADHD. Neither medication class is a complete answer on its own when both conditions are active.
Current guidance leans toward prioritizing whichever condition is most impairing or unstable at the time of treatment, then building an integrated plan that layers psychotherapy with medication as needed rather than picking one diagnosis to treat in isolation. In practice, that often looks like:
Monitoring matters more here than in a single-diagnosis case, because a medication change aimed at one condition can shift the other. A clinician tracking both pictures at once, rather than treating them in sequence without communication between providers, tends to get to a stable plan faster.
The clinical literature on this overlap has grown substantially, and a few studies carry particular weight for anyone trying to understand their own symptoms or prepare for an assessment.
| Study focus | Key finding | Source |
|---|---|---|
| Comorbidity prevalence | 25% to 50% of people with ADHD also meet criteria for an anxiety disorder; 27.9% of an anxiety clinic sample met ADHD criteria | Pmc |
| ASRS discriminant validity | Some ASRS items, especially in the hyperactivity factor, poorly distinguish ADHD from anxiety symptoms | Adult ADHD Self-Report Scale study |
| Treatment patterns | ADHD patients with comorbid anxiety or depression had more frequent medication changes and higher healthcare costs over 12 months | Treatment Patterns claims analysis |
These findings point toward the same conclusion from different directions: comorbidity is common, standard screening tools have real limits when anxiety is present, and getting the diagnosis wrong has measurable downstream costs in treatment time and money. Research in this area continues to evolve, and no single study or tool replaces a clinician’s judgment built on a full history and direct conversation with the person in front of them.
When a presentation doesn’t fall neatly into one category, we start with a thorough intake rather than a quick screening checklist. That means targeted use of validated tools alongside a careful look at childhood history, school records where available, and input from people who’ve known you across different periods of your life. We find that pattern, not a single questionnaire score, is what clarifies the picture.
We offer both online and in-person assessment options, with direct billing available to a wide range of insurers so cost isn’t a barrier to getting answers. For anyone unsure whether their concerns even warrant a full assessment, a free connection call with a therapist is a low-pressure way to talk through what you’re noticing before committing to anything further.
— Deane
Sorting out whether ADHD, anxiety, or both are behind your symptoms isn’t something to figure out alone from a list of overlapping traits. Our ADHD assessments are built around the same clinical markers covered here: childhood history, cross-setting impairment, and a full picture rather than a single screening score. We also offer anxiety counselling and online counselling for anyone who’d rather start the conversation from home, and family-focused support through our family therapy for ADHD services when a loved one’s attention or anxiety challenges affect the whole household.
A few practical advantages make starting easier: every new client can book a free connection call with a therapist before committing to anything, we offer direct billing to a wide range of insurers so paperwork doesn’t slow things down, and no physician referral is required. We also offer appointments across our Calgary, Red Deer, and Cold Lake locations for anyone juggling a full schedule.
Before booking, it helps to jot down a few concrete examples of how your symptoms show up at work, at home, and in relationships, along with anything you remember or have heard about your childhood behavior. If you’re ready to get clarity on what you’re experiencing, our individual counselling and therapy team can help you book an assessment and start building a plan that actually fits what’s going on.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
The clearest sign is what happens when you’re calm and doing something you enjoy: if your attention sharpens in those moments, anxiety is likely driving your inattention, while persistent distractibility regardless of mood points toward ADHD. A professional evaluation that reviews your childhood history and symptoms across multiple settings is the only reliable way to know for certain.
Severe anxiety typically includes persistent, hard-to-control worry, physical symptoms like a racing heart, sweating, or muscle tension, and in some cases full panic attacks with sudden, intense fear. Sleep disruption, irritability, and difficulty concentrating often accompany these core symptoms, especially when worry escalates around specific triggers.
ADHD and anxiety frequently occur together, with research estimating that 25% to 50% of people with ADHD also meet criteria for an anxiety disorder. The relationship runs in both directions: the chronic stress of living with unmanaged ADHD can fuel anxiety, while anxiety itself can worsen attention and working memory.
Many adults with ADHD manage their symptoms effectively through a combination of treatment, structure, and support, and go on to build stable careers and relationships. Getting an accurate diagnosis, especially when anxiety is also present, is often the turning point that makes day-to-day functioning noticeably more manageable.
Related reading: How anxiety counselling helps, Panic attack or anxiety attack?, How to get diagnosed with ADHD in Alberta and ADHD assessment for women.